

Abdominal wall surgery: see all conditions and techniques
Medical information: Dr Pablo Aragó Chofre, specialist in General and Digestive Surgery. Read about his professional background.
Repairing an incisional hernia involves more than making a lump disappear: the aim is to reconstruct the abdominal wall weakened by a previous operation. The eTEP and PeTEP endoscopic techniques allow this reconstruction to be carried out through small incisions, with the mesh positioned outside the peritoneal cavity. Robotic assistance extends the range of tools available for dissection and suturing.
The surgical technique is chosen individually, taking into account the hernia, your health and your previous medical and surgical history. During your consultation, we agree on a treatment plan and explain its benefits, risks and recovery.
On this page: eTEP and PeTEP · Robotic surgery · Recovery · Request an assessment
What is an incisional hernia, and why does it need careful planning?
An incisional hernia develops when a gap forms in the abdominal wall at the site of a surgical scar. Fat or abdominal contents protrude through this defect. It may cause tightness, pain, difficulty with physical effort or a change in the shape of the abdomen that becomes more noticeable when standing. It can also develop in the scar from a laparoscopic incision.
The size of the lump alone does not show how complex the repair will be. The width of the opening, the number of defects along the scar and the position of the muscles all matter. If there have been previous repairs, we also need to know where the mesh was placed and how the tissues have changed.
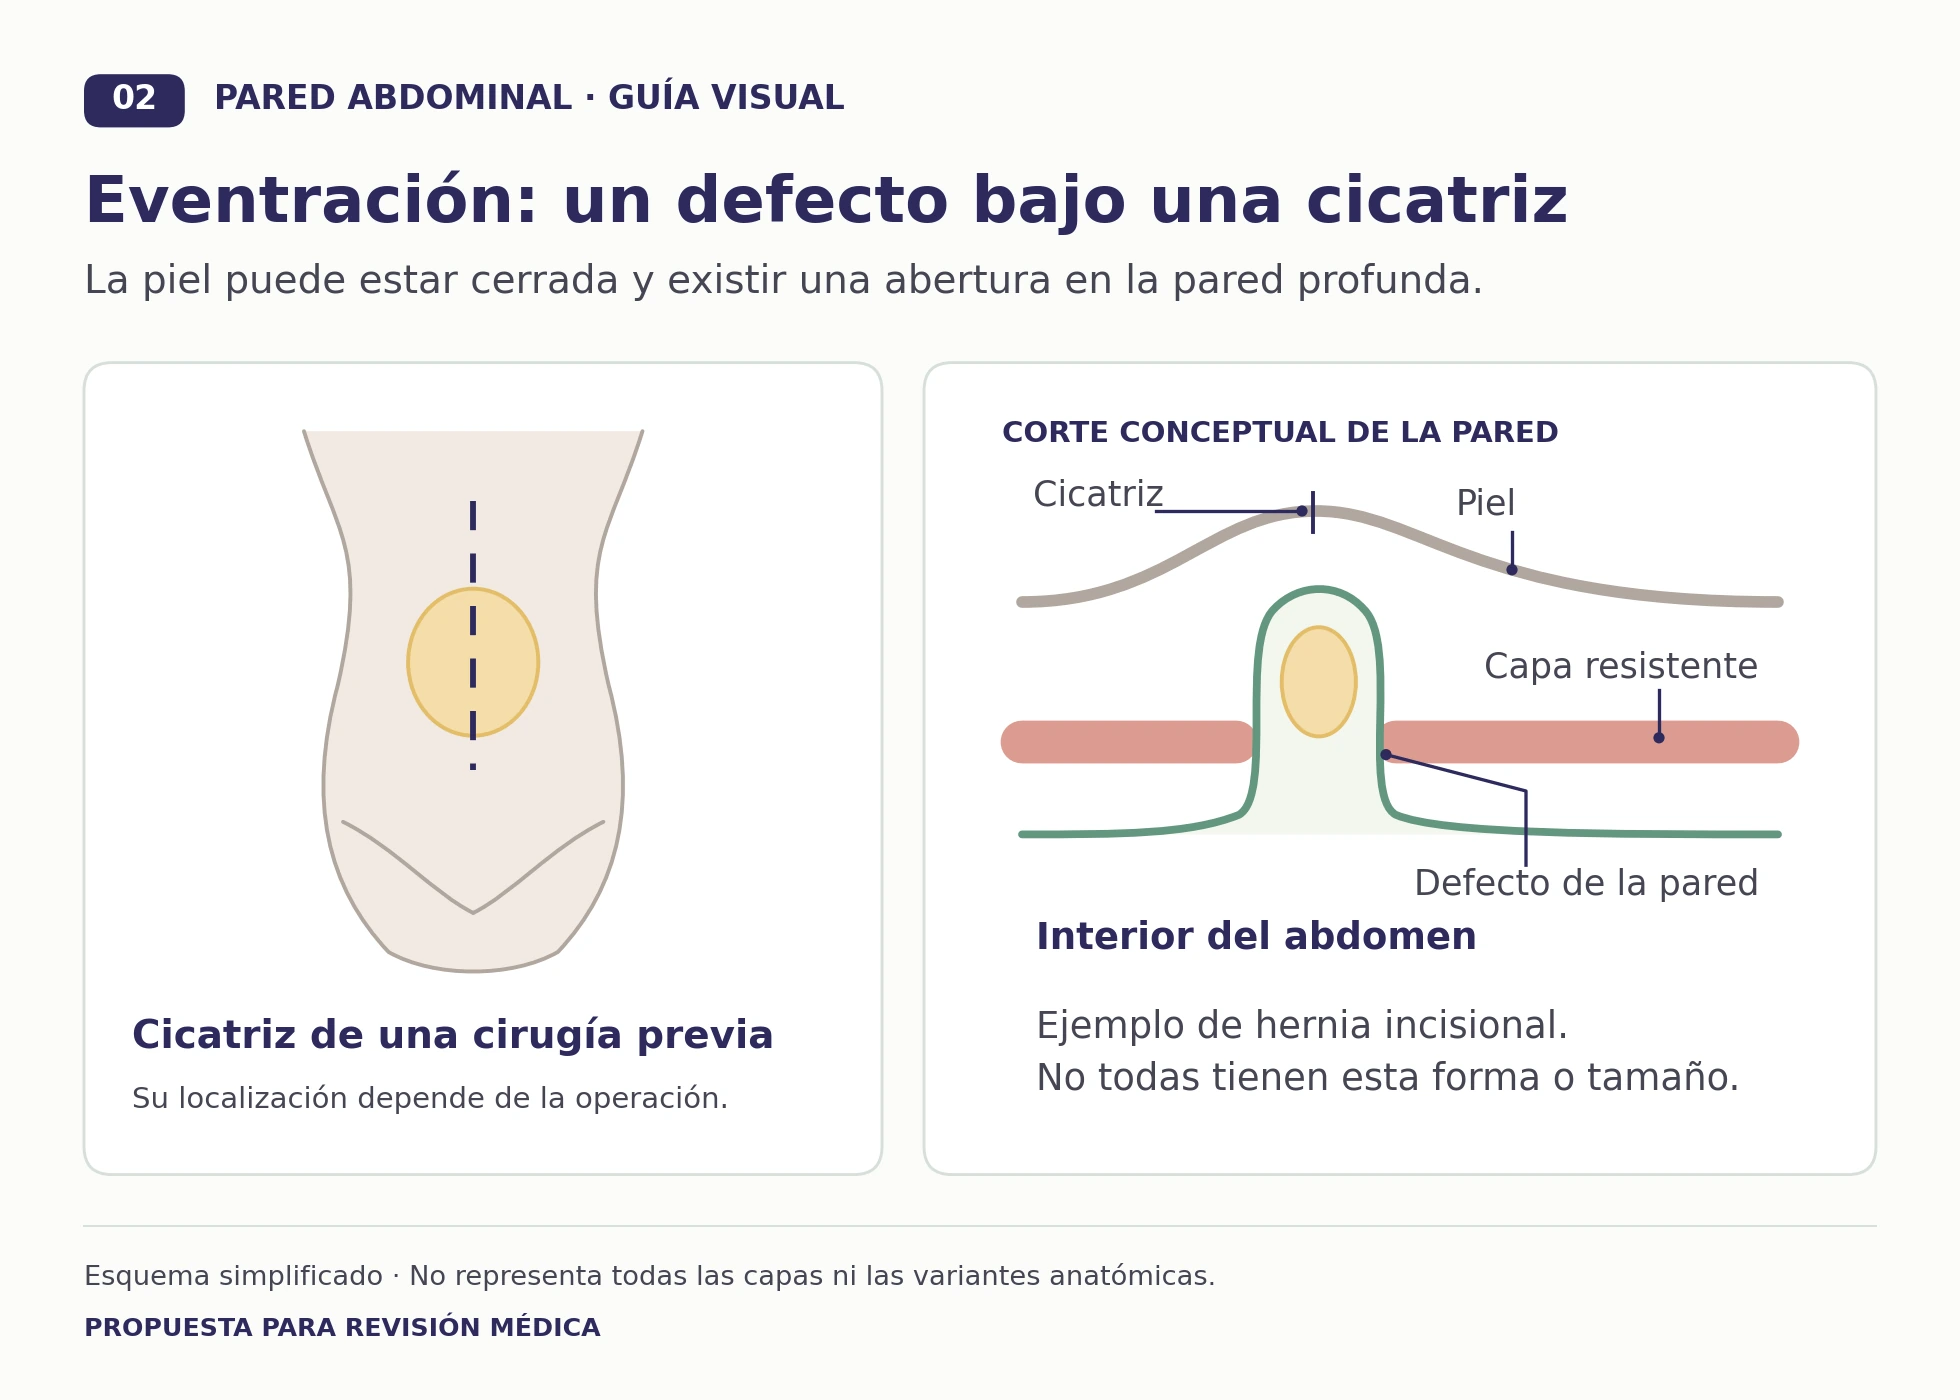
Enlarge the incisional hernia diagram.
Endoscopic reconstruction: repairing within the abdominal wall
The aim is to restore continuity of the abdominal wall and reinforce it with a sufficiently large piece of mesh. Extraperitoneal techniques create a working space between the layers of the wall, rather than leaving the implant directly exposed to the abdominal organs. The access incisions are small, although the internal repair may cover a considerable area.
eTEP Rives–Stoppa: reconstruction behind the muscles
The eTEP technique creates an extraperitoneal working space using a camera and endoscopic instruments. In a Rives–Stoppa reconstruction, the retrorectus plane behind the rectus muscles is prepared, the midline is reconstructed and the mesh is positioned in that space. This applies the principles of a retromuscular repair through small incisions.
PeTEP: repair in the preperitoneal plane
PeTEP develops the space in front of the parietal peritoneum, the membrane lining the inner surface of the abdominal wall. Through this access, the defect is repaired and the reinforcement is placed outside the peritoneal cavity. Its difference from a retrorectus reconstruction lies in the plane of dissection, rather than simply the size of the incisions. It is a recently developed technique, with less long-term comparative evidence than established approaches.
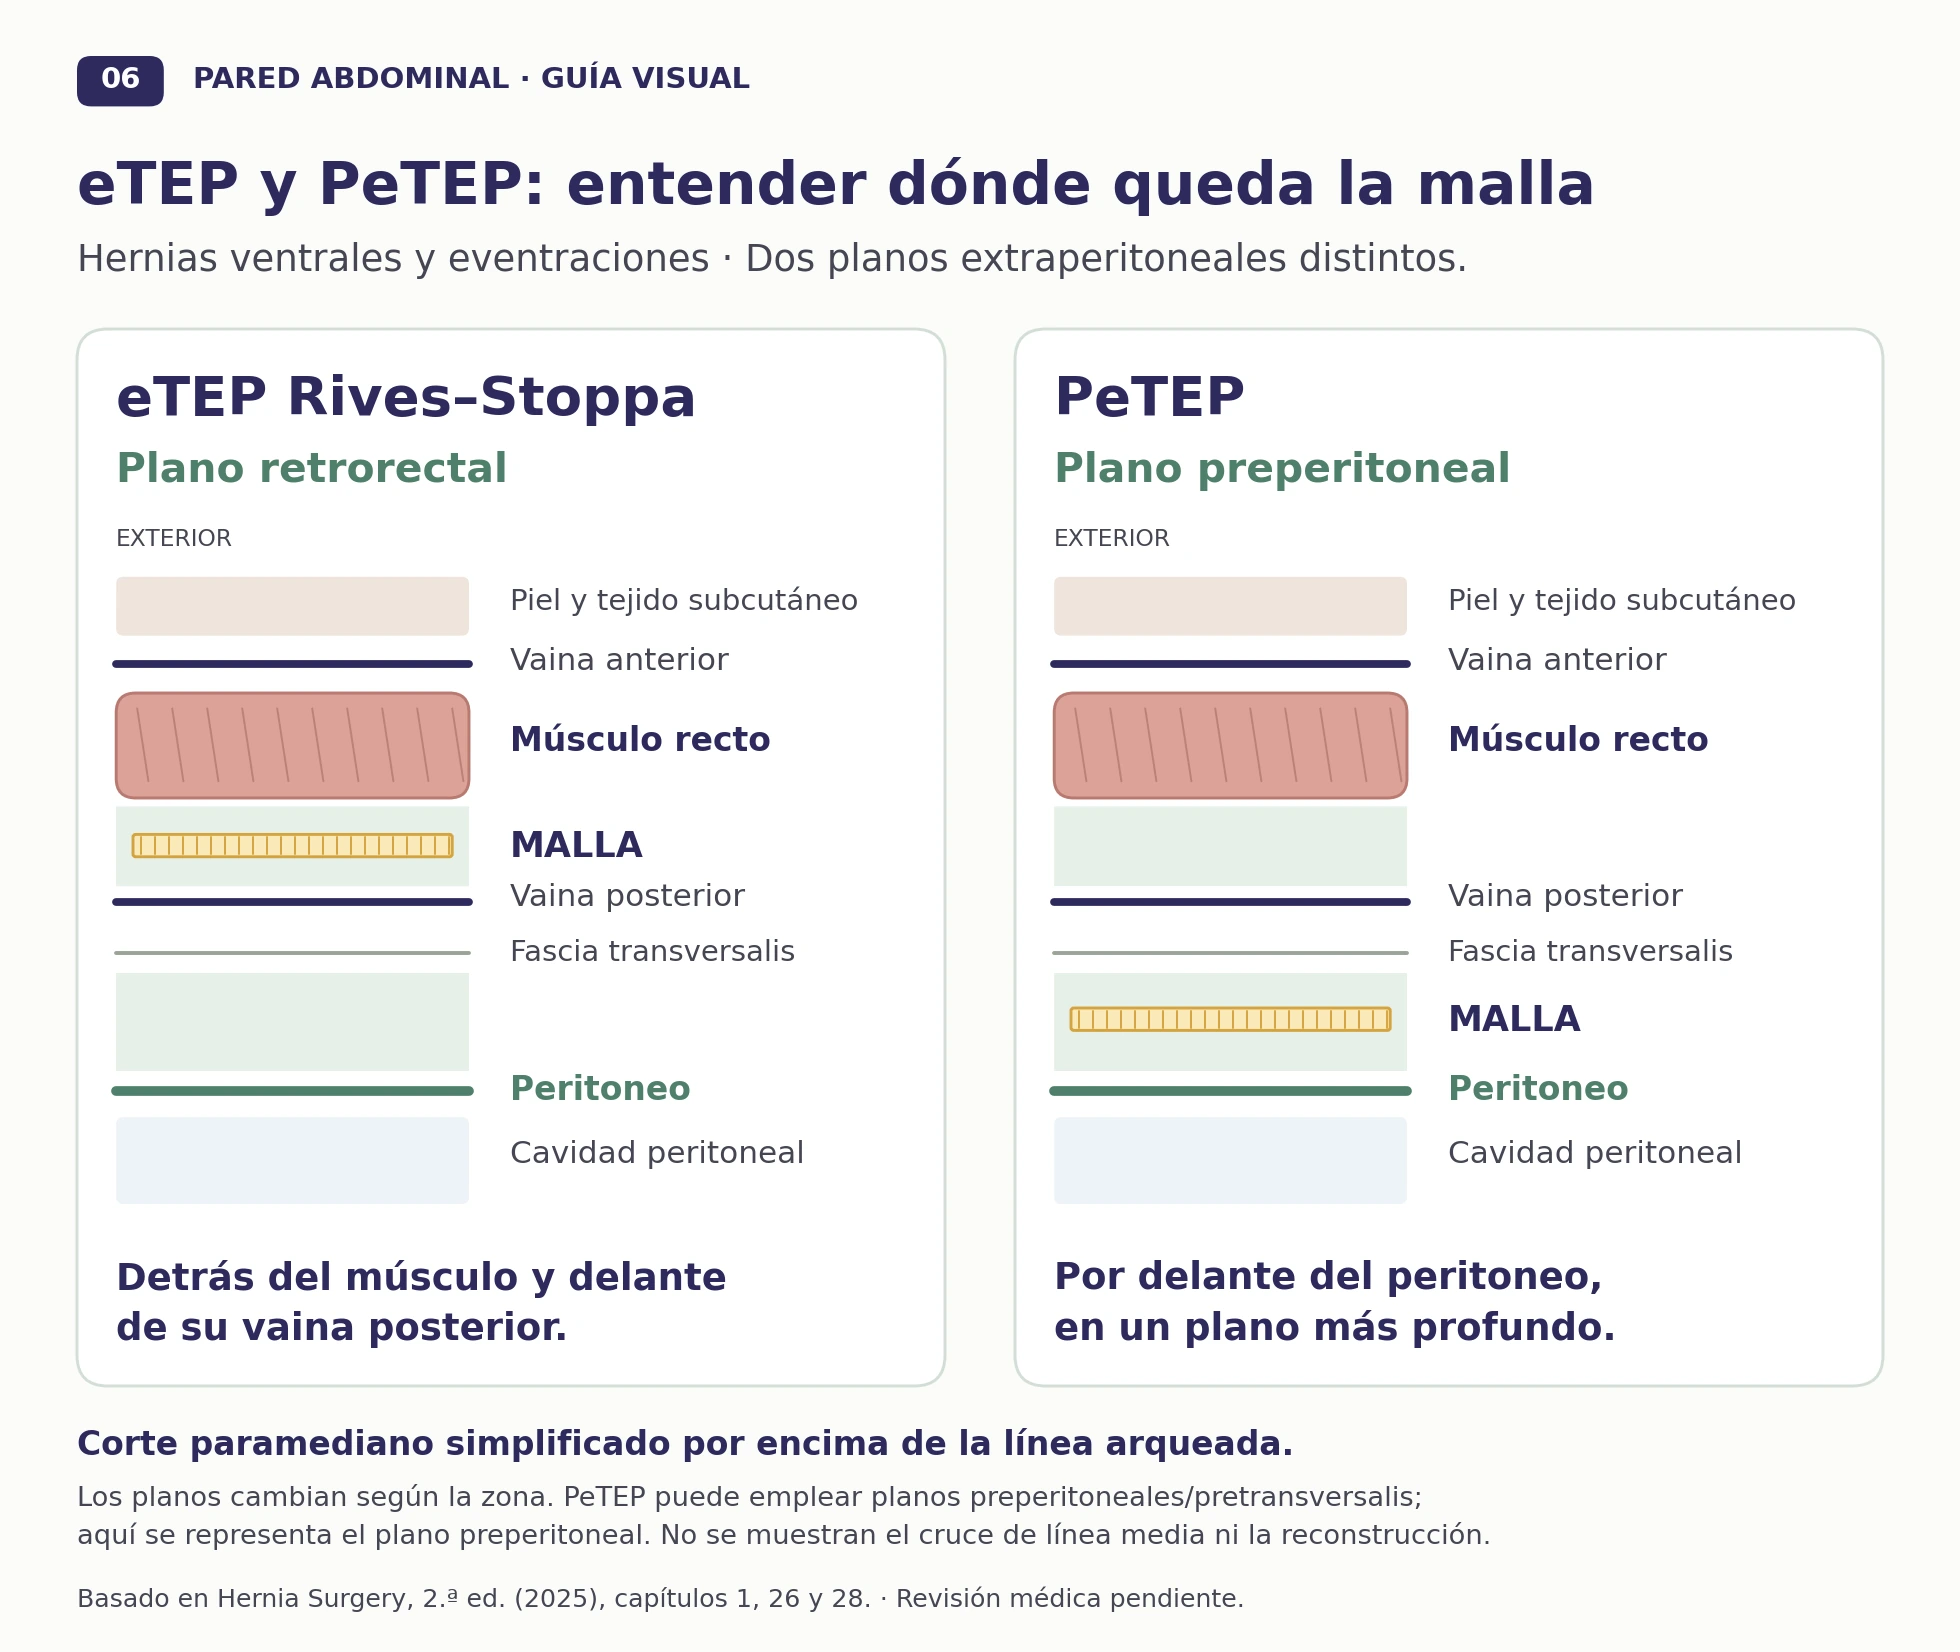
Enlarge the eTEP and PeTEP repair planes.
Ventral TAPP or vTAPP
vTAPP initially enters the abdominal cavity laparoscopically. From there, the peritoneum is opened, the preperitoneal space is prepared for the repair, and this layer is closed again over the mesh. Like extraperitoneal approaches, it aims to separate the implant from the abdominal organs, but it reaches the repair plane by a different route.
What robotic assistance adds
In robotic eTEP and PeTEP repairs, the surgeon controls articulated instruments and a camera from a console. The movement of these instruments helps the surgeon work within the spaces of the abdominal wall and place stitches, an important part of reconstructing the midline and closing the layers that cover the mesh.
The robot does not choose or perform the operation by itself. The repair follows anatomical principles; the platform is one way of carrying it out. Equipment availability is confirmed when the operation is scheduled and does not guarantee fewer complications or a faster recovery.
A CT scan as a map of the abdominal wall
When planning incisional hernia surgery, a CT scan allows us to measure the defect, identify other openings and assess the muscles, the contents of the hernia and previous repairs. This information helps define the extent of reconstruction and assess whether the edges can be brought together. Reports from previous operations complete this picture.
Preparing the patient is also part of treatment
Stopping smoking, improving diabetes control and addressing weight or nutritional problems help prepare the body for healing. Before a planned repair, we identify which factors should be improved and over what period, taking into account your symptoms and how the hernia is changing. Waiting indefinitely is not without risk either if the defect grows or increasingly limits activity.
When an open repair is used
An open Rives–Stoppa repair places the mesh in the retromuscular plane through an incision; an open preperitoneal repair is another option. These approaches remain necessary when treating an extensive scar, performing a complex reconstruction or working with tissues that make an endoscopic approach difficult.
When the edges cannot be brought together without excessive tension, abdominal wall release techniques such as component separation or TAR may be needed. These are advanced reconstruction steps that require specific planning; they are not part of every incisional hernia repair.
What to expect during recovery
The size of the skin wounds does not fully reflect the work carried out inside. An endoscopic reconstruction also involves internal stitches and a large area of healing tissue. Early movement is encouraged and pain relief is prescribed; returning to lifting or strenuous activity is planned according to the extent of the repair.
A seroma may develop: a collection of fluid in the area where the hernia was, which can feel like a lump without necessarily meaning that the hernia has returned. Follow-up appointments assess the wound, pain and changes in that area. Other risks include a haematoma, infection, injury to abdominal structures, persistent pain and recurrence of the hernia.
When to arrange a consultation and when to seek emergency care
An incisional hernia that is growing, painful or limiting daily life should be assessed at a planned consultation. Some incisional hernias that cause few symptoms can be monitored with follow-up. If the lump becomes very painful and no longer goes back in, or you develop vomiting, abdominal swelling or changes in the skin, seek urgent medical attention.
Incisional hernia consultation in Valencia
Bring your surgical reports and any available scans. We will review the anatomy of your abdominal wall, the options for endoscopic or robotic reconstruction, and the preparation needed before surgery. Read about Dr Pablo Aragó's professional background.
Request an appointment at your preferred IMED centre: Valencia (Burjassot), Colón or Gandía. In the booking portal, select Cirugía General y del Aparato Digestivo (General and Digestive Surgery) and Dr Pablo Aragó Chofre. If you need help or cannot find his appointments, see the telephone numbers and locations of the three centres.
The button opens IMED's external booking service, which has its own terms and privacy policy. Your appointment is subject to confirmation by the centre. Do not use this channel for emergencies.
More about abdominal wall surgery: Abdominal wall surgery · Minimally invasive inguinal hernia surgery · Umbilical and epigastric hernias
Medical sources
EHS midline incisional hernia guidelines, 2023. This information provides general guidance and does not replace an individual assessment.
Review of the evidence on PeTEP, 2026.
Anatomical basis of the diagrams: Novitsky YW (ed.), Hernia Surgery: Current Principles, 2nd edition, 2025. Original illustrations based on the book; they do not reproduce its figures.